Tuesday, October 10, 2017

Dandy Walker Malformation and Hydrocephalus: Is there a connection?


What is Dandy-Walker malformation (DWM)? (Part I)
1 cerebellum and the ventricular system
1
Walker-Walburg
Syndrome
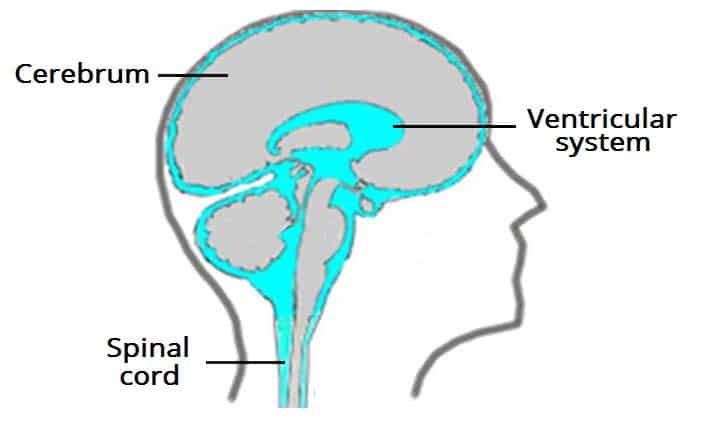
Dandy-Walker malformation (DWM) is a malformation of the brain which occurs during the embryonic development phase of the of the cerebellum and the fourth (4th) ventricle. The cerebellum (pictured at right) is the portion of th7e brain that, not only helps in the coordination of movement, but also is involved with both cognition and behavior. The fourth (4th) ventricle is a space around the cerebellum that channels cerebrospinal fluid (CSF) to the outside of the brain. DWM is characterized by underdevelopment (both a small size as well as an abnormal position) of the middle part of the cerebellum known as the cerebellar vermis, Additionally, it causes cystic enlargement of the fourth (4th) ventricle as well as enlargement of the base of the skull (Posterior fossa). In approximately twenty percent (20%) to forty percent (40%) of DWS cases, it occurs as the result of hydrocephalus (see: What is Hydrocephalus (Part 1 of 2) and What is Hydrocephalus (Part 2 of 2)). In addition to hydrocephalus, DWM can also be mistaken for Walker-Warburg Syndrome (WWS) (pictured above left). WWS is a rare, genetic, multisystem disorder characterized by muscle disease and eye abnormalities. Although the specific symptoms vary from case to case, the most consistent features of WWS are a smooth appearance to the surface of the brain (due to the lack of normal folds known as Lissencephaly), malformation of other brain structures such as the cerebellum and the brain stem, various developmental abnormalities of the eyes, and progressive degeneration and weakness of the voluntary muscles (Congenital muscular dystrophy). WWS is considered to be a form of muscular dystrophy and is inherited as an autosomal recessive genetic condition.
DWM affect approximately one (1) birth per 25,000 - 35,000 live births in the United States and affects the male population more than the female population.
What causes DWM
DWM is caused by defects which occur early in the embryonic development of the cerebellum and surrounding structures. in a few patients chromosome abnormalities including the depletion of 3q24.3 (which is the location of the first DWM genes known as ZIC1 and ZIC4), 6p25 or 13q32.2q33.2, or the duplication of 9p. In the remainder of cases, it is due to more complex genetic and, perhaps, environmental factors or Teratogens. 
Related disorders
Symptoms of other conditions (outlined below) can be similar to (and mistaken for) DWM. These include:

Hydrocephalus

Hydrocephalus is a condition where abnormally widened (dilated) ventricles inhibit the flow of cerebrospinal fluid (CSF). This results in a build-up of the CSF in the skull causing pressure on the brain. 

Walker-Warburg Syndrome (WWS)

WWS is a rare, genetic, multi-system disorder characterized by both muscle disease as well as eye and brain disorders. Specific symptoms and severity of WWS vary from person to person, however, the most consistant feature is a smooth appearance of the surface of the brain due to the lack of normal folds (lissencephaly) as well as malformation of other brain structures

Primary care needs of children with hydrocephalus


Last night I was on Facebook and reading messages in one of the hydrocephalus support groups I subscribe to. The mom of a hydrocephalic child asked a question about ventriculo-peritoneal (VP) failure and constipation; being I have this blog, I started researching and found LOTS of articles, the only problem was you had to pay to view anything more than the abstract. Not to be deterred, I did another search this morning and found an article that presented enough information that I can intelligently respond to her question. To accomplish this, I am going to discuss the primary care needs of children with hydrocephalus and include the information about the VP shunt and constipation.

Clinical manifestations at the time of diagnosis


Although the signs and symptoms of hydrocephalus might be somewhat varied due to the specific cause of the condition, there are common clinical manifestations associated with the increased intracranial pressure (ICP) (See Magnetic Resonance Imaging (MRI) at right). If the accumulation of excess cerebrospinal fluid (CSF) occurs slowly, the child may be asymptomatic until the hydrocephalus is quite advanced. Because of this, significant dilation of the ventricle(s) can occur before abnormal growth of the head is apparent. A myriad of symptoms including: 1) Full (or distended) fontanels; 2) Frontal bossing (protruding forehead); 3) Prominent veins in the scalp; 4) Vomiting; 5) Irritability; and 6) Opisthotonic posturing might be observed before dramatic changes are noted in head circumference.


Roona Begum, age 5, was one of the
more severe cases of hydrocephalus.
In older children - where the cranial sutures have already fused - the development of hydrocephalus might result in the non-specific symptoms of headache, nausea, vomiting, and personality changes (including irritability or lethargy) might occur. In addition, spasticity or Ataxia (complete loss of control of a specific body part) or urinary incontinence can occur in more severe cases. The child might also experience vision problems such as extraocular muscular paresis (caused by increased pressure on the second, third, or sixth cranial nerves) and/or papilledema. If the increase in intracranial pressure occurs near the hypothalamus, alterations in growth, sexual development, or electrolyte imbalance may occur.

Associated problems

Constipation is not a secondary problem I would have associated with hydrocephalus, but turns out it is. To be completely accurate, it is not the problem per se, but, rather the elevated intraabdominal pressure which, in turn, places pressure on the distal end of the shunt (pictured at right) (Journal of Neurosurgery: Pediatrics, 2006). According to Constipation as a reversible cause of ventriculoperitoneal shunt failure there have been two (2) documented cases (including imaging evidence) of children with apparent VP shunt failure who were also severely constipated. Treatment of the constipation resulted in both clinical and imaging-documented resolution of the shunt failure.

Seizures occurring during infancy are not uncommon at the time of the initial diagnosis of hydrocephalus due to the increased intracranial pressure (ICP). An estimated twenty percent (20%) of infants with hydrocephalus continue to experience seizures after their first year of life. These seizures can be either simple or complex in nature (up until age eight, I suffered from absence seizures where my awareness and responsiveness were impaired) and are typically well-managed with standard anticonvulsant therapy. By contrast, seizures that occur with acquired hydrocephalus are more likely to result from the underlying cause (such as a brain tumor or infection) and are more difficult to treat.

The effects on intellectual function is difficult to determine early on in the disease process. The cause of the hydrocephalus seems to be the crucial point in determining how it - intelligence - will be affected. If the hydrocephalus is uncomplicated, it generally has a better prognosis than hydrocephalus resulting from a brain injury. In recent studies, two-thirds (2/3) of children diagnosed with hydrocephalus had normal or borderline normal intelligence (for reference purposes, 85 - 115 is considered normal). In children - with hydrocephalus - with an intelligence quotient (IQ) score above 70, their performance IQ scores are lower than full-scale and verbal IQ. This discrepancy indicates a need for both pre-school and school counseling and testing to identify areas of learning disability.


Visual abnormalities are often found either at the time of diagnosis or in the event of a shunt malfunction. The increase in intracranial pressure (ICP) result in optic nerve pressure, limited upward gaze (also known as Sunset sign or Parinaud's syndrome), extraocular muscle paresis, and Papilledema (shown at right).


Although their shunt is completely functional and their hydrocephalus is controlled, these children commonly suffer from vision problems such as strabismus (misalignment of the eyes), amblyopia (commonly known as "lazy eye" where the brain favors one eye over the other), nystagmus (rapid, uncontrollable movement of the eyes) or astigmatism (blurred vision resulting from an irregular surface contour of the cornea). Refractive and accommodation error is seen in between 25% - 30% of children with hydrocephalus.

Motor disabilities are seen in approximately 75% of children diagnosed with hydrocephalus. These can range from severe paraplegia (paralysis of the legs and lower body as a result of spinal injury or disease [such as hydrocephalus]) to weakness or mild imbalance. The severity of the motor deficit is usually dependent on the diagnosis; for example, a child diagnosed with porencephaly (a cyst filled with cerebrospinal fluid [CSF] forms within the brain) or Dandy-Walker Malformation (DWM) tends to have more serious motor defects than a child with "simple" congenital hydrocephalus.

Fine motor control is also affected by hydrocephalus.  Kinesthetic-proprioceptive abilities of the hands are often affected negatively and, coupled with impaired bimanual manipulation and frequent visual deficits, make it difficult for a child with hydrocephalus to perform well on time-limited, non-verbal intelligence tests.

Primary care management

Growth and development

Both precocious and short stature have been documented in children with hydrocephalus. Sexual development prior to the age of eight (8) in girls and the age of ten (10) in boys is considered precocious and warrants additional diagnostic study. Height below the 5th percentile, if not compatible with family stature, is an indication of growth retardation. Treatment is available for both of these conditions and the child should be referred to an endocrinologist is symptoms of either condition persist.
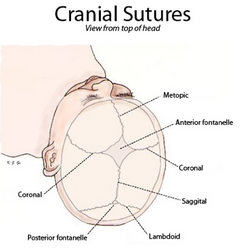
If a child is suspected of having hydrocephalus, their head circumference should be measured by an experienced medical professional. Until the cranial sutures (pictured at left) are completely fused - which can be delayed in a child with hydrocephalus - any increase of head size is a major indicator in diagnosing the child's condition. Once placement of a shunted has been completed, head circumference may decrease by one to two centimeters as the intracranial pressure (ICP) is relieved. Following this initial decrease, the child's head should grow in proportion to the child's body.

Standard infant developmental screening tools utilized in a primary care practice (such as the Denver Developmental Screening Tool) may be of little help when assessing an infant with hydrocephalus. It is important for the child's practitioner to interpret developmental findings in the context of clinical observations so as to assist the parent's in developing reasonable expectations for the infant. Some motor delays are to be expected during infancy and early childhood due to an estimated 75% of children with hydrocephalus having some form of motor disability. The primary care provider (PCP) should carefully document the acquisition of motor skills because the loss of these skills can be an indication of shunt malfunction or progression of the causation of the hydrocephalus. Additionally, ataxia, slurred speech, or a lack of progression in school can be an indicator of the deterioration of neurological status and a need for further evaluation.

Immunizations

Diphtheria, Tetanus, Pertussis (DPT) is an important immunization for a child with hydrocephalus because pertussis (commonly known as whooping cough) can cause a unique problem for the hydrocephalic patient. However, caution must be exercised due to the fact that infants with a history of seizures are at a higher risk of suffering a seizure after the vaccine is administered. For this reason, deferring this immunization until neurological stability is ascertained is advisable.

The measles vaccine has also been implicated in in post-vaccination seizures (in children with hydrocephalus) particularly if they have a previous history of convulsions. Seizures that occur post-vaccination are not believed to result in damage and, combined with the ongoing high risk of natural measles, justifies use of the vaccine even if the child has a previous history of seizures.

Haemophilus influenza type B (or HIB) is recommended for all children at eighteen (18) months of age. Due to an increased risk of HIB infection in a child with a shunt, they should definitely receive the vaccine as recommended.

For additional information: Primary care needs of children with hydrocephalus, VP shunts and constipation

References

Journal of Neurosurgery: pediatrics (2006).  Constipation as a reversible cause of ventriculoperitoneal shunt failure. Retrieved on October 2, 2017 from thejns.org/

Microcephaly: the exact opposite to hydrocephalus

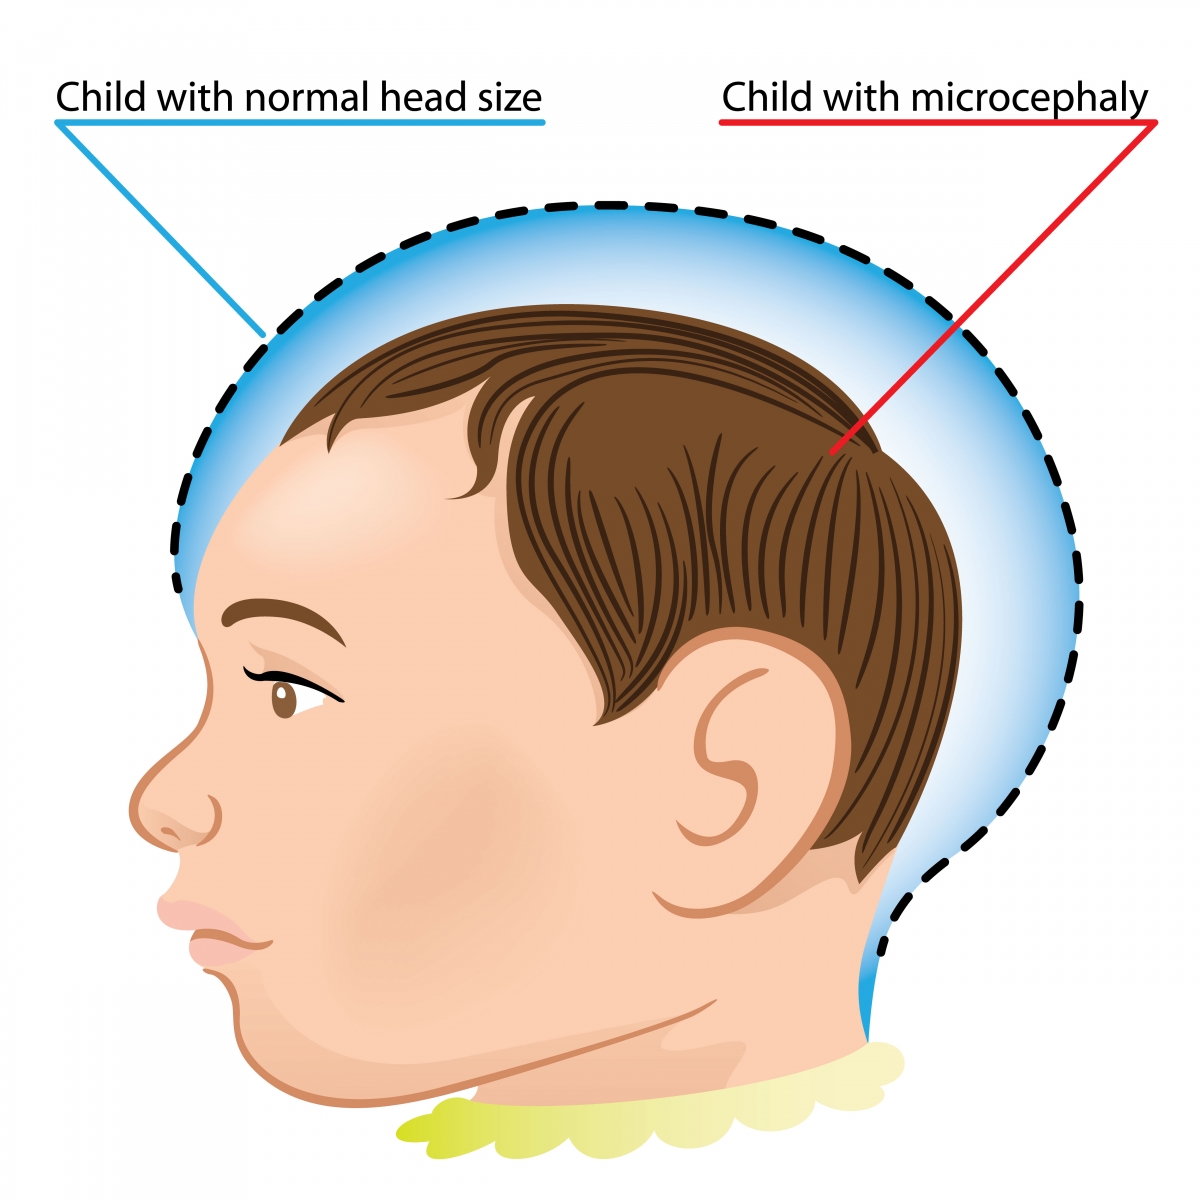
The blue shaded area represents the head size of
a normal size head (22.5" for a male baby) compared to a child with
microcephaly
What is microcephaly

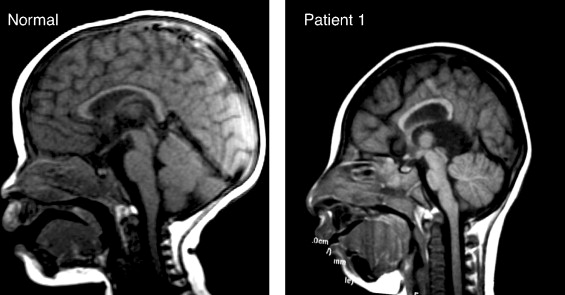
The word microcephaly comes from micro plus the Greek word kephale meaning head which literally translates to micro (or small) head. The Centers for Disease Control (CDC) defines microcephaly as a birth defect that results in a smaller than average head (when compared to babies of the same age and sex). As might be expected, their brain tends to be smaller than average and might not have developed properly.

A normal size brain (left) and a brain affected
by microcephaly (right).
According to CDC researchers, the smaller head is the result of the child's brain not developing properly while the infant was in-utero or growth stopped shortly after birth. In approximately fifteen percent (15%) of cases a child born with this condition can have a normal life expectancy (and near normal intelligence), however, in severe cases they have a reduced life expectancy and poor brain function.

Microcephaly is not a common condition. According to state birth defect tracking systems, it occurs in somewhere between two (2) babies per 10,000 live births and twelve (12) babies per 10,000 live births.

How and when can it be diagnosed

Diagnosis during pregnancy can sometimes be accomplished by use of an ultrasound examination. If this process is used, it should be done either late in the second (2nd) trimester or early in the third (3rd) trimester.

Diagnosis after the baby is born is done by measuring the circumference of the newborn's head as part of a routine medical exam. The provider compares this measurement against population standards according to sex and age. It (microcephaly) is defined as "a head circumference measurement that is smaller than a certain value for babies of the same age and sex". This measurement value is usually less than two (2) standard deviations below the average. The measurement value might also be designated as less than the 3rd percentile. This means that the baby's head is extremely small compared to babies of the same age and sex.

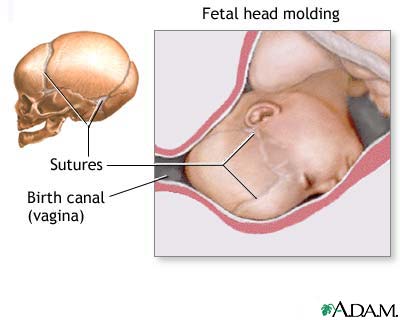
Microcephaly can be diagnosed by measuring head circumference (HC) after birth. Although HC can be influenced by molding of the head (where pressure from the birth canal "molds" the head into an oblong rather than round shape [pictured at right]), measurement should still be taken on the first day of life because commonly used birth head circumference charts are based on measurements taken before 24-hours of age.

What are the causes of and risk factors for microcephaly

Sadly, the cause of microcephaly in most infants remains unknown. In some cases, it was determined to have been caused by a change in their genes  Research by the CDC has shown that exposure to the following during pregnancy can lead to the condition:

Certain infections during pregnancy including rubella, toxoplasmosis, or Cytomegalovirus.

Malnutrition which could either be from not getting enough food or not getting the proper nutrients.

Exposure to harmful substances such as alcohol, certain drugs, or toxic chemicals.

Interruption of the blood flow to the baby's brain during development.

Babies born with microcephaly have been reported among mother who were infected by the Zika virus while pregnant. As a result, CDC researchers have been able to determine that exposure to the virus can cause microcephaly as well as other severe fetal brain defects.

Other problems associated with microcephaly

Babies with microcephaly can experience a myriad of other problems depending on the severity of the microcephaly. Common problems include: seizures, developmental delay(s) (such as with speech, sitting, standing or walking), intellectual disability, problems with movement or balance, feeding issues (such as difficulty with swallowing), hearing loss, or vision problems.

These problems can range from mild in nature to extremely severe to the point of being debilitating. Because the brain is small and undeveloped, babies with severe microcephaly tend to have more of these problems than a baby with milder microcephaly. Severe microcephaly can be life-threatening. Because it is difficult at birth to predict exactly which problems the baby will face, they will require close follow-up with their health care provider to monitor their growth and development.

How is microcephaly treated?

It is a life-long condition. Currently, there is no known cure - or standardized treatment - for microcephaly. Because symptoms can range from mild to severe, treatment options can also vary. For example, if a baby is born with mild microcephaly, they might only experience a smaller-than-normal head; still, that child will require routine check-ups to monitor their growth and development.

 For more severe cases, babies will require care and treatment that focuses on managing the associated health problems. Additionally, developmental services delivered early in the child's life can both improve and maximize the child's physical and intellectual abilities.

For additional information: Facts about Microcephaly


Sunday, October 1, 2017

Hydrocephalus and the individualized education program (IEP) (Part 2 of 2)


Part one of this blog looked at how the individualized education program came into existence and the process by which a child is evaluated. Part two will look at how the IEP is customized for each student and the steps taken to make sure it is being effective.

III. Designing the IEP

If a student is diagnosed with a disability, the next step is to design a program for him or her that addresses their unique needs. This program will be laid out in a very specific, very long document called the individual education program or IEP (pictured at right). It is reviewed annually. Just for clarification, an initial IEP must be in place within thirty (30) days following the evaluation meeting to determine eligibility; afterwards, an annual meeting must, under the terms of PL 94-142, take place no later than 365 days later. Meetings held after the 365 day benchmark are considered non-compliant.

IV. What goes into the IEP

As the old saying goes "everything but the kitchen sink". All brevity aside, keep in mind that the IEP is a binding document for the provisions of service between the district and the parents. This means that if the district does not provide the services promised in the IEP, it is non-compliant with not only the IEP, but also the law. Inside the IEP, a parent can expect to find the following:

Present levels are a snapshot of who the student is and how he/she is doing. It should include data such as reading test scores and math test scores, current grades, observed skills, behavioral referrals, and a record (or records) of work habits.

The offer of Free and Appropriate Public Education or FAPE which is commonly referred to as "placement" and/or "services". This is the binding part of the contract - between the parents and the district - where the district offers classroom or ancillary services such as speech therapy. It should also specify how often (number of days in the school year) the student will receive these services as well as the duration (how many minutes each session will last). Variable terms such as "as needed" cannot be used in this section, rather it should specifically spell out the minimum number and times for provision of services.

Goals are written to provide a measure of progress. They can be academic, social, or behavioral and should always be written with recognized area of need in mind. These goals should be achievable and measurable (see: S.M.A.R.T. goals)

Accommodations and modifications are changes to the classroom environment which may be necessary to assist the student (see example at left). For those who might not be familiar with the difference between these two terms, an accommodation helps a student to complete the same work on the same level as his/her peers; a modification allows for the student's work to be changed or completed on a different level.

Recent legislation mandates requires a transition plan if a student who will turn 16 years-old within the life of the IEP. The legislation also requires a transition goal in addition to the transition plan.

Typically each member of a student's IEP team signs a signature page and meeting notes that 1) Indicates their presence at the meeting; and 2) He or she approves the notes taken during the meeting. In addition, the parent(s) must consent to the accommodations, modifications, and placement (offer of FAPE) from the district for the initial IEP to be implemented.

V. What happens at the IEP meeting

As I indicated above, by law, this meeting must take place once-a-year and is designed to bring all of the team members together to discuss the student's needs as well as to review his/her performance by reviewing their progress toward stated goals. This is also when the teams reviews the student's eligibility to continue services and is known as the Triennial review and must be completed once every three years.

Just as an interesting sidebar about the IEP meeting, many new teachers are under the mistaken impression that the entire IEP must be written during this annual meeting. While some of the writing does happen during this meeting, the team should be prepared to come to the meeting with a first draft of goals, present levels, suggested accommodations, and an offer of Free and appropriate public education (FAPE).

Additional information: Individualized education program (IEP)

Thursday, September 28, 2017

Hydrocephalus and the individualized education program (IEP) (Part 1 of 2)


I. How did it all begin?

Although the legal precedence for inclusion can be traced back to Brown v. Board of Education (347 U.S. 483 [1954]), it was really the parent's of children with a disability that encouraged legislators to adopt the  Education for All Handicapped Children Act (EAHCA) (PL 94-142) in 1975 which required school district's to both include and educate children with special needs as well as to create specialized academic plan (later to be known as an individualized education program or IEP) for them.

Because of its honorable beginnings, it only makes sense that the IEP (sometimes also referred to Individualized Education Plan) process was intended to be centered on the student. That being said, which students qualify for an IEP? Below is a listing of the disabilities or impairments that are eligible for an IEP: Autism, Deaf-blindness, Deafness, Emotional disturbance, Hearing impairment,  Intellectual disability, Multiple disabilities, Orthopedic impairment, Other health impairment, Specific learning disability, Speech or language impairment, Traumatic brain injury and Visual impairment.

II. Having your child / student evaluated for an IEP


For a parent, it is very simple if you believe that your child is qualified to receive special education services. It's just a matter of going to their teacher, principal, or the school's psychologist. Once you have asked about you child being evaluated for an IEP , a group of qualified personnel (including those outlined above) will decide whether or not an evaluation is warranted and create an appropriate plan if an IEP is deemed necessary. From the time the parent gives consent to proceed with the evaluation, the district has sixty (60) days to complete the evaluation. Any decision regarding the IEP evaluation must, by law, include parental input.

It should be noted that a child's teacher can also refer students for evaluation, but only after attempts have been made to remedy the problem without special education services. If such attempts have been made (and the student is continuing to struggle), the next step is initiation of an intervention under RTI (response to intervention) or convening the school's student services team (SST) to discuss their performance. In this meeting, the general education teacher brings samples of the student's work as well as supportive data such as reading scores and math scores, behavioral charts, and writing samples. From this data, the team can decide whether the student would benefit from an evaluation, or if they should continue without special education services.

 If the suspected cause of the problem is the result of a learning or behavioral impairment, the SST can work together to determine what tests need to be done and what data needs to be gathered. This can include a variety of performance-based tests such as Woodcock Johnson, Third Edition (WJIII), or the Wechsler Individual Achievement Test (WIAT). In addition, they might perform cognitive function and behavioral function testing.

Following this testing (and gathering of existing information), the evaluation team will meet again to discuss the results of the tests. At this time, if a decision is made regarding evaluation, the student's parent(s) are invited to participate.

I would be amiss if I did not include the caveat that there are certain diagnosis that neither teachers or school psychologist are not qualified to make. These include Attention Deficit Hyperactivity Disorder (ADHD), Autism (or Autism Spectrum Disorder), as well as most physical and developmental delays require a medical diagnosis. If you are an educator and suspect that you have a student affected by one of these conditions, it is imperative to include a medical professional in the evaluation process.

To sum up this portion of the IEP process, in each category of disability, there must be an impact on the student's education that is directly attributable to the disability and they must be deemed in need of specially designed instruction. After all, not all children with a disability require special education services.

For additional information: Individualized education program (IEP), Summary of PL 94-142

Monday, September 25, 2017

What is slit ventricle syndrome (SVS)?


I. Understanding our ventricular system
brain parenchyma

One error that we make in considering the ventricular system of the human brain is that it is static and that the ventricles do not modify over time. This is not true and evidence of this can be seen even before birth by viewing a prenatal ultrasound where they are relatively small. What is the ventricular system? Simply put, it is a communicating network of cavities filled with cerebrospinal fluid (CSF) located within the brain parenchyma (pictured at right). It is made up of two (2) lateral ventricles, the third ventricle (the site used for an endoscopic third ventriculostomy or ETV), the cerebral aqueduct, and the fourth ventricle. Additionally, the choroid plexuses - responsible for the production of CSF - are located within the ventricular system.

The the downside of this dynamic ability is the fact that the ventricles tend to grow larger as we age because of a decrease in the number of brain cells. The good news about this increase in size (except in extreme cases) is that the actual size of the ventricular system appears to have little affect on the function of the brain.

One interesting fact that I wasn't aware of until I began reading for this blog is the fact that each time our heart beats a shock wave is produced that changes both the shape and size of the ventricles. This dynamic change can be monitored using magnetic resonance imaging (MRI) which pinpoints a specific sequence.

II. What are slit ventricles


Simply put, they are small ventricles (often so small that they are barely visible on either a computerized-axial tomography (CT) scan (pictured at left) or an MRI. They can occur following a severe head injury or a viral infection of the brain. In either case, the brain becomes so swollen that fluid is literally pushed from them.

Another phenomena that is of interest to the medical community is the fact that they are often seen following cerebrospinal fluid (CSF) diversion such as accomplished by a implant of a shunt. Interestingly that condition (decompression of the ventricular system) is one of the benchmarks of a properly functioning shunt system and is confirmed by comparing a post-implant CT or MRI with one done prior to the implant. In some cases, this decrease in the size of the ventricular system results in a "siphoning" effect. How the brain physically reacts to this siphoning is largely dependent on the patient's age. In young children, the brain is still very watery and easily changes shape. Unfortunately this effect is very unpredictable and and very little can be done to affect it one way or the other.

It is important to understand that small / slit ventricles do not always cause symptoms -- some patients are asymptomatic (showing none of the usual symptoms) and go for long periods never knowing they have a problem. Typical symptoms associated with small / slit ventricles include: 1) Headache; 2) Lethargy that can vary in intensity from mild to debilitating; 3) Nausea and vomiting. These symptoms can be intermittent and the headache is often relieved by laying down.

III. What is slit ventricle syndrome

Slit ventricle syndrome (SVS) is a grouping of symptoms which, for example, can occur in a patient in a patient with a functional shunt, but whose brain has lost some of its elasticity. As I mentioned above, they might experience headache, vomiting, and drowsiness / lethargy which, interestingly enough, are the same symptoms experienced when a person with hydrocephalus is having a shunt malfunction. One thing that makes SVS symptoms slightly different is the fact that they are VERY cyclical in nature often with like clockwork. As an example, the patient can be perfectly fine for three (3) weeks and then become violently ill, sleep for 24-hours, and then be "normal" again. Generally, there is no cause for the symptoms experienced, although a minor viral infection has been known to act as a triggering mechanism.

Under normal circumstances, the shunt drains the CSF from the ventricles to another part of the body - such as the peritoneal cavity - for reabsorption. In certain patients, however, this causes the ventricle(s) to collapse. In a person who is shunted this cause the ventricle to collapse on the ventricular catheter blocking it off and preventing the outflow of CSF and causes the appearance of symptoms. Due to the fact that the brain has lost some of it's elasticity (due to the original condition that caused the hydrocephalus) the ventricles are slow to return to their normal size causing symptoms to persist.

IV. How is SVS treated

Once symptoms have manifested themselves, the most important thing to determine is whether the shunt is functioning properly and not having intermittent blockages due to a malfunction within the system. In many cases, this can be as easy as measuring the intracranial pressure (ICP) within the skull. Once the functionality of the shunt is assessed, the next step is to consider a volume expansion procedure such as a subtemporal decompression. This procedure involves removing a small section of bone from the skull which allows the ventricle - and the catheter - to expand and relieves the excess pressure.

Saturday, September 23, 2017

Hydrocephalus and college: dreaming the possible dream (Part 2 of 2)


III. Who needs to know (about your hydrocephalus)

First and foremost, you should tell your new roommate(s) about your hydrocephalus simply because they are the one person you will be around the most during your academic career. It's best to inform them about it within the first few days after classes begin so that they will know what to expect and, more importantly, how they can help you in the event a situation arises where you need their assistance. It is also a good rule of thumb to let your resident advisor or guidance counselor about your hydrocephalus because they can guide you about who - if anyone - needs to be aware of your hydrocephalus. As you explain your hydrocephalus to your roommate and/or RA/counselor, make them aware of the signs and symptoms of a shunt malfunction so that they can assess your condition if you're unable to do it for yourself. It is also a good idea to make them aware of where you keep the file folder/notebook with information relevant to your condition. Lastly, ask your roommate or RA/counselor if they would be comfortable accompanying you to the hospital in the event a problem occurs. This will facilitate notification of your family and assure treatment is rendered in a timely manner.

Whether or not you inform your professor(s) about your hydrocephalus is a decision best made once made in the first few days of a new quarter / semester. Even if you have previously registered with your school's disability resource center (DRC), your instructors aren't made aware of your condition unless you decide to tell them.

IV. Tips and advice

Academics


I could write an entire blog about academics and those of us with hydrocephalus but one of the important thing to remember is - while researching schools you wish to attend - is to determine what services they offer for students with a learning disability. If you had an Individualized Education Program (IEP) in place during high school, your team should be meeting with you to assist in negotiating your transition.

Medical experts recommend that the beginning of your college years might also be a good time to schedule a neuropsychological examination. such an exam can pinpoint your learning strengths (and weaknesses) as well as guide you on what classes might be the best tailored to your learning style and ability.

As I stated above, make sure to contact your school's DRC  and let them know that you have hydrocephalus.  The staff in the DRC can assist you with any accommodations you might need such as extra time to complete exams or tutoring services.

Broken tubing in a
ventriculo-peritoneal
shunt
Alcohol

Let's be real college students (for the most part) experiment with alcohol. Although there is no known correlation between being shunted and experiencing an adverse reaction to alcohol, studies have proven that drinking in excess is not good for anyone. This is especially true for those of us with hydrocephalus (and particularly if you are shunted). I say that because the symptoms associated with a hangover (headache, lethargy, nausea, and vomiting) are also seen in the event of a shunt failure. The key difference being the symptoms of a hangover normally subside after several hours; if they persist - and you have a shunt - you should seek medical attention to prevent a potentially life-threatening situation.

Consumption of alcohol can also adversely affect your medications. While some simply loose their effectiveness, others can result in extreme drowsiness and other potentially dangerous side effects. The best rule of thumb is: if you take medication(s), don't drink alcohol.

Headaches

As strange as it sounds, headaches are often times a fact of life for many young people. The combination of deadlines, finals, too much junk food, and irregular sleep patterns can trigger a headache, however, if you are hydrocephalic, such an event could potentially be life-threatening. Even for the most knowledgeable person with hydrocephalus, it can be difficult to differentiate between a regular headache and a headache resulting from a shunt malfunction and/or failure. As a general rule, if the headache improves after taking a couple of Tylenol and resting for a short time, it is not coming from your shunt or as a result of your hydrocephalus. If a headache persist (or you have that "gut feeling" that something is not right) seek medical attention because it's better to be safe than to be sorry.

Additional information: College and hydrocephalus