Showing posts with label Pressure. Show all posts

Monday, September 4, 2017

Did you know? Some interesting information you might not be aware of regarding shunts and hydrocephalus


I. Highs and lows

A fellow hydrocephalic posted on Facebook that if there is a storm approaching, she tends to become very lethargic. That made me curious, so I did some research and hydrocephalus (particularly if the person is shunted) tends to be effected by changes in the weather. According to published research, fluctuations in barometric pressure can affect people who suffer from headaches such as those of us with hydrocephalus. It is interesting to note that the study particularly addressed this phenomenon as it applies to migraine sufferers, however, it stands to reason that if it affects someone who suffers from migraines, it would also affect someone with hydrocephalus. According to the National Hydrocephalus Foundation, the majority of persons with hydrocephalus - and who are shunted - will be affected periodically by an approaching weather system (particularly if it's an area of low pressure). Symptoms accompanying this "feeling out of sorts" include having no energy as well as being unable to concentrate. If it develops into a full-blown headache, the best remedy is to find a dark, comfortable place and ride out the storm. The good news is, once the area of low-pressure causing your distress is directly overhead, symptoms will cease almost immediately.

II. Recovery from surgery

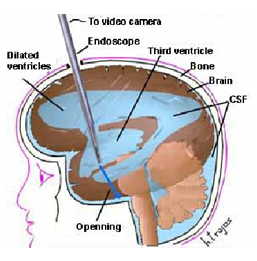
People who have had an endoscopic third ventriculostomy (ETV) or a shunt implant usually have a four (4) to six (6) week recovery period before they begin to feel like themselves again. The biggest thing patients experience is getting their strength back and the best way to speed up is to take short walks - sound down the block and back - and gradually increase your distance as your stamina improves. Perhaps equally as important as exercising your body post surgery, is to exercise your mind. For those who enjoy playing cards, medical experts say that a game of solitaire, bridge, or even poker will do wonders to improve short-term memory.


For additional information: Patient-to-patient: tricks of the trade 

Saturday, September 2, 2017

Normal pressure hydrocephalus: the "grown-up"version of an under-recognized problem (Part 3 of 3)


In part two of "Normal pressure hydrocephalus: the "grown-up" version of an under-recognized problem" we looked at what causes 
 normal pressure hydrocephalus or NPH and how it is diagnosed. In part three we will explore what treatment options are available.

V. What treatment options are available?

Just like its counterparts acquired hydrocephalus and congenital hydrocephalus,the only available treatment is surgical implant of a shunt (pictured at right). Most shunt systems consist of three (3) components: 1) A collection catheter (the ventricular catheter in the picture at right); 2) A valve mechanism that controls how much CSF flows through the system; and 3) An exit catheter (the peritoneal catheter in the picture at right) to drain the CSF to another part of the body where it can be absorbed -- in this instance, the peritoneal cavity in the abdomen. In most cases of NPH, the most common shunt implant is a peritoneal shunt and the most commonly used system is the ventriculoperitoneal system which goes from the cerebral ventricle to the peritoneum. Alternatively, the drainage catheter can also be placed in a vein that leads to the heart known as a ventriculoatrial or VA shunt. With either system, once the implant surgery is completed, all components of the shunt system are entirely under the skin.

The shunt valve is a critical component of the system and the design that has been in use is the differential pressure (DP) valve. It operates by the valve opening when the (fluid) pressure at the inlet of the valve exceeds the (fluid) pressure at the outlet by a preset amount.  In adults with hydrocephalus, the valve is sometimes overwhelmed by the effects of gravity, leading to the drainage of too much CSF. The common name for this over-draining is siphoning. In some cases the patient is asymptomatic while others experience headache or nausea while in an upright position. In extreme cases it can also result in so much CSF being drained that it causes subdural hematoma. To counteract this problem, valve mechanisms have been designed that incorporate both anti-siphoning and gravity-compensating mechanisms. The anti-siphoning mechanism component is triggered by a change in the CSF pressure while the gravity-compensating mechanism is triggered by postural changes.

For additional information:

NPH booklet

Sunday, August 27, 2017

Normal pressure hydrocephalus: the "grown-up"version of an under-recognized problem (Part 2 of 3)


In part one of "Normal pressure hydrocephalus: the "grown-up" version of an under-recognized problem" we looked at what normal pressure hydrocephalus or NPH is and what symptoms are experienced. In part two, we will look at what causes it, how it is diagnosed, and what treatment options are available.

III. What causes normal pressure hydrocephalus?
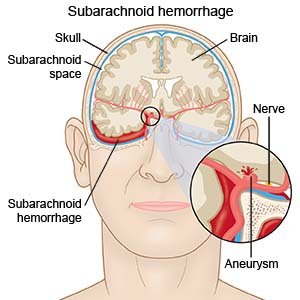
In the majority of normal pressure hydrocephalus (NPH) cases are classified as idiopathic meaning that it occurs spontaneously or that the exact cause is unknown. It should be noted, however, that there are known causes for NPH including: head injury, cranial surgery, subarachnoid hemorrhage, tumor, or cyst. Additionally, it can result from subdural hematoma, bleeding that occurs during surgery, or meningitis. It is interesting to note that all of the causes outlined above can predispose the patient to inflammation (which affect the cerebrospinal fluid [CSF] pathways) which impedes the CSF flow.

IV. How is NPH diagnosed?

In many cases, it is often the affected person or close family member who first brings the symptoms of NPH to the attention of a doctor. Additionally, there have been cases where the enlarged ventricles have been found on a brain image (such as a CT scan) that is performed for a totally different reason. If a physician has reason to suspect his/her patient has NPH, the doctor can order a variety of test to confirm this diagnosis.

Once NPH is suspected by the affected person's physician, it is imperative that a neurologist, neurosurgeon, or neuropsychologist be brought on board. Their involvement from the diagnosis stage onward is helpful not only from the standpoint of interpreting test results, but also in discussing the surgical option (if indicated), potential side effects and follow-up care.

As the diagnostic process moves forward, the decision to order a specific test might hinge on the given clinical situation. These might include, but are not limited to:

Clinical exam to evaluate symptoms consists of an interview (with the patient and their family) and/or a physical/neurological exam. (Hyperlink goes to a YouTube video.)

It is important to note the presence of the Hakim triad of symptoms is not necessary to confirm a diagnosis of NPH. The medical team will consider both the pattern and severity of impairments (combined with the results of other tests outlined below) to differentiate NPH from other possible outcomes.

CSF tests to predict shunt responsiveness and/or determine shunt pressure include lumbar puncture ("spinal tap"), external lumbar drainage, measurement of CSF outflow resistance, intracranial pressure (ICP) monitoring, and isotopic cisternography (pictured at left).

Lumbar puncture allows for an estimation of both the CSF pressure as well as analysis of the fluid. Performed under a local anesthetic, a thin needle is passed into the spinal fluid space of the lower back. The doctor then removes up to one (1) cubic centimeter (cc) of CSF are removed to see if a reduction in CSF volume relieves symptoms being experienced by the patient.

External lumbar drainage (also known as continuous lumbar drainage) is a variation of the lumbar puncture where a flexible catheter is left in place to facilitate drainage of the CSF. It allows for either continuous or intermittent drainage of CSF over several days to emulate the effect a shunt would have. It also allows for a more accurate reading of CSF pressure as opposed to the "moment in time" measurement provided by the lumbar puncture.

For intracranial pressure (ICP) monitoring or spinal pressure monitoring a small pressure monitor is inserted through the skull into one of three places: 1) The brain itself; 2) The ventricles of the brain; or 3) The lumbar region to monitor ICP. It is utilized to detect an abnormal pattern of pressure waves as well as either low or high pressure. The results from this testing can be utilized to select an initial pressure setting if a shunt is being implanted.

Isotopic cisternography is no longer frequently used because a "positive" cisternography result does not reliably predict whether the patient will respond to implant of a shunt and the (cisternography) results are often ambiguous.


For additional information: NPH booklet

Friday, August 25, 2017

Does it hurt? Hydrocephalus and the headaches associated with it (Part 1 of 2)


The other evening I was looking at what I had written about so far and thinking of additional topics when a long-time friend suggested "anything but the typical 'does it hurt' '" that she and I have heard too much as we grew up with a disability and even now as we are in our adult years. Following her comment, I began looking and came up with the idea of doing a blog on hydrocephalus and the associated headaches suffered by some of us.

I. Mechanics of hydrocephalus and headaches

The combination of brain volume (volume for the average adult is 1,260 cubic centimeters), blood volume, and cerebrospinal fluid (CSF) volume determine intracranial pressure or ICP. If one of these increases, pressure in the brain will rise unless one of the others compensates by decreasing. In a person - such as myself - with hydrocephalus this balance is distorted and a unnatural condition takes place. In a person not affected by hydrocephalus, they should have one ounce (1 oz.) of CSF in the ventricles and about four ounces (4 oz.) of CSF surrounding the outside of the brain. When the components of the brain are functioning normally - without a shunt - the brain has the ability to be elastic. This means it is able to compensate accordingly for an increase (or decrease in CSF pressure). In hydrocephalus patient's who have been shunted, this is no longer the case.

No automatic alt text available.
Physiology of hydrocephalus
In studying to present this blog, I learned something that I had never heard before and that is that when our bodies enter rapid eye movement (REM) sleep (typically about 80 - 90 minutes after falling alseep) plateau waves occur resulting in increased intracranial pressure (ICP). In shunted patients who undergo ICP monitoring overnight, those changes are considerably more drastic that with the average person. Those things that would normally be expected to cause an increase in ICP result in huge changes in a shunted patient.

Placement of a shunt results in an unnatural situation. The brain fills the intracranial space while the shunt drains essentially of the available CSF from the ventricles.The end result is a larger-than-normal brain in a fixed (NOT elastic) skull with little room for changes in the ICP (which is characteristic of a person with hydrocephalus. If changes in blood flow occur, resulting in blood volume within the intracranial space, increased intracranial pressure will occur and can result in a headache.

Headaches can also be the result of altered pressures within the skull once a shunt has been implanted. Interestingly, the can occur both if the pressure is too high or too low.

II. Treatment

Like everyone else, both children and adults with hydrocephalus experience periodic headaches. It is the frequency and severity of these that determine whether they are a result of the hydrocephalus. According to Dr. Gordon McComb, Chief of Neurosurgery, Children's Hospital Los Angeles, "If the headaches are getting progressively worse, many times it's an intermittent malfunction of the shunt". Dr. McComb explains that ventricle size is also not always an accurate indication of whether the shunt is working correctly. "The ventricles are going to remain the exact same size whether the pressure is normal or elevated".

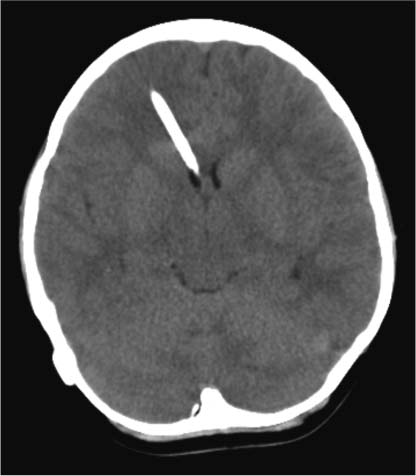
The slit ventricle is the white streak
visible pointing toward the
left side of the brain
With slit ventricle syndrome, small ventricle size is not the cause of the problem. The problem occurs if the shunt becomes clogged and the ventricles don't dilate. If this situation happens repeatedly (accompanied by acceleration in the occurrence of headaches) it can indicate a blockage the builds up and then releases. Replacing the proximal ventricular catheter in the shunt will normally correct this problem.

When hydrocephalus problems experience repeated headaches it is imperative to sketch out a plan of action which involves a conference between the patient and his/her doctor(s). This conference sets up treatment parameters and, if those parameters are exceeded, the medical team moves forward with the replacement of the shunt.


For additional information: Hydrocephalus and headaches

Thursday, August 24, 2017

Normal pressure hydrocephalus: the "grown-up"version of an underrecognized problem (Part 1 of 3)

Image result for normal pressure hydrocephalus


Before I go any further into my topic, I will ask my reader's to please not take offense at the illustration above. It is a light-hearted way to explain the effects of a condition that affects an estimated 700,000 Americans and often goes undiagnosed and untreated. According to the Hydrocephalus Association, an estimated 80% of cases remain unrecognized by the medical community.

I. What is normal pressure hydrocephalus (NPH)?

Many people aren't family with the term Hydrocephalus but, if you refer to it as "water on the brain" they immediately know what you are referring to. In older adults it manifests itself as Normal pressure hydrocephalus or NPH. The term "water" is a misnomer, however, because the substance that creates the problem is cerebrospinal fluid (CSF). As the CSF builds up, it can cause dangerously high intracranial pressure (ICP) and affect how the brain functions. There are a number of factors that can cause NPH including: head injury, surgery, or a brain bleed (hemorrhage).

II. What are the symptoms of NPH?

Image result for salomon hakimThe term Normal pressure hydrocephalus was first coined by Dr. Salomon Hakim (pictured at right) in his 1964 paper which spoke of a type of hydrocephalus where there is little or no increase in the ICP and occurred primarily in older adults. One thing that made NPH so dramatically different from other forms of hydrocephalus was what Dr. Hakim referred to as the triad of symptoms. These are: 

Gait disturbances which can range from a mild imbalance to a total inability to stand or walk at all. Often described as a "magnetic gait" characterized by wide-based, short steps with a noticeable shuffle. Additionally, persons with NPH might have problems picking up their feet making the navigation of curbs and stairs difficult and placing them at a higher risk for falls.

Mild dementia can be described as the loss of interest in activities, becoming forgetful, difficulty performing daily routine tasks, and short-term memory loss. Typically these symptoms are less severe than those seen with full-blown dementia and are often overlooked for years or dismissed as a consequence of aging. Persons with NPH usually do not  (emphasis added) lose language skill, but their deficits might not be as obvious to them and they might deny there is even a problem.

Impairment of bladder control is usually characterized by both urinary frequency and urgency, however, the complete loss of bladder control (urinary incontinence) can occur in more severe cases. As a point of education, urinary frequency is a need to urinate more frequently -- sometimes as much as every one to two hours. Urinary urgency is the strong, immediate sensation of the next to urinate. In some cases, this urge is so strong that it cannot be held back resulting in incontinence. In very rare cases, fecal incontinence can also occur.


For additional information: Hydrocephalus facts and stats, NPH article NPH booklet